Structured for how clinicians actually write. One continuous clinical record — from high-acuity specialty care to multi-problem GP.
Most scribes turn a consult into wordy medical-student prose or fragmented flashcards. Intelligent Consult captures complex clinical speech — in the room, on telehealth, or dictated after — and writes a single continuous record in true consultant shorthand for you to review and finalise.
Free for everyday use (up to 8 sessions/day · 60/month) · Mac, Windows, Web, iPhone & Android
High-acuity speech & clinical shorthand accuracy
Captures rapid multi-speaker consults, drug regimens, physiological trends, and Australian shorthand (/7, /52, /12, c/o, O/E, PMHx, NKDA) without flattening clinical nuance.
Written like a senior consultant — not an AI medical-student essay
Zero demographic preambles ('The patient is a 45-year-old who reports...') and zero filler prose. Clipped telegraphic facts, numbered problem lists, and explicit differential weightings.
One continuous clinical record, ready for your EMR
No fragmented flashcards. Your note renders as a single continuous clinical sheet with inline subheadings — capturing complex shared decision-making and ceiling-of-care boundaries verbatim.
Emergency Physician Consult
Built for undifferentiated resuscitation, competing differentials, bedside PoCUS, time-stamped ED interventions, and explicit escalation thresholds.
Why senior clinicians notice the difference
Documents physiological trajectory, why competing differentials are weighted up or down, and resus escalation boundaries.
Templates in this family
“Six days post-laparoscopic hemicolectomy with sudden pleuritic chest pain and presyncope, HR 118, BP 96/62, bedside echo shows dilated RV and McConnell's sign, CTPA confirms saddle PE — systemic lysis carries high surgical-site bleed risk so we've discussed IR catheter thrombectomy and ICU admission with the patient and his wife.”
Triage information
Acute dyspnoea, pleuritic chest pain & borderline hypotension · Triage Cat 2 · Ambulance arrival to Resus Bay 2.
History
Sudden-onset R pleuritic chest pain and progressive SOB 4 hr prior, 6/7 post-laparoscopic hemicolectomy for colonic adenocarcinoma. Transient presyncope standing at home; nil haemoptysis, nil calf pain.
Past medical history
- Stage II colon Ca - HTN - Paroxysmal AF — apixaban held 5/7 peri-op, restarted yesterday
Medications
- Perindopril 5mg mane - Apixaban 5mg bd - NKDA
Examination
- Alert, anxious, speaking in short phrases; GCS 15, afebrile (T 36.8) - HR 118 sinus tachycardia, BP 96/62 (MAP 73), RR 28, SpO2 91% RA -> 96% on 4L NP - CVS: HS dual, loud P2, JVP +4 cm, peripheries cool - Resp: chest clear bilaterally, nil wheeze or crepitations - Abdo/LL:laparoscopic port sites clean/dry, abdomen soft; R calf +2.5 cm vs L, mild deep tenderness
Investigations
- VBG: pH 7.45, pCO2 29, lactate 2.9, Hb 121 - ECG: sinus tachycardia 118 bpm, S1Q3T3 pattern, TWI V1–V3 - High-sensitivity troponin I: 84 ng/L (elevated), BNP: 640 pg/mL, Cr 108 (baseline 88) - Bedside PoCUS: dilated RV (RV:LV ratio >1.0), McConnell's sign positive, IVC 2.3 cm non-collapsing, nil pericardial effusion - CTPA: large saddle pulmonary embolism extending into bilateral main lobar branches with right heart strain
ED management
- 2x 18G IV access, continuous telemetry + invasive radial arterial line - Cautious 250 mL Hartmann's bolus -> BP 102/66, HR 110 - Unfractionated heparin IV bolus 80 units/kg + infusion commenced per high-risk PE protocol - Systemic thrombolysis (alteplase 10mg bolus + 90mg over 2 hr) prepared at bedside given recent abdominal surgery (<7/7)
Assessment
1. Intermediate-high risk submassive saddle pulmonary embolism with RV strain (sPESI 2, troponin/echo positive) 2. Relative contraindication to systemic fibrinolysis (6/7 post-colectomy) — high major bleeding risk vs haemodynamic decompensation
Shared decision making
Discussed diagnosis of high-risk clot on the lungs and the balance between clot-busting medication (high risk of internal surgical-site bleeding given recent bowel surgery) versus targeted catheter extraction and ICU monitoring with the patient and spouse. Patient opted for urgent interventional radiology catheter thrombectomy pathway and ICU admission, with systemic thrombolysis reserved for rescue if acute haemodynamic collapse occurs.
Disposition
Admitted to ICU under Respiratory/PERT (Dr V. Menon accepting); proceeding directly to IR suite for mechanical thrombectomy.
Same workflow when it is not a consult
Non-clinical sessions don't require a practitioner declaration — meetings, interviews, and workplace conversations work for anyone.
Watch it in real clinical rooms
From GP consults to busy ED bays and dual-screen telehealth.
Pick a clinical setting below and tap play to watch (and hear) how Intelligent Consult captures the conversation and structures the finished draft.
Look at your patient — not your keyboard.
Leave the mic on in the consult room or dictate a quick summary after. OLI structures History, Examination, and Plan in seconds and supports 55 languages.
What this film shows (GP Consult Note · 55 Languages)
- ✓Eye contact in the consult instead of typing while the patient talks
- ✓Structured History, Examination, and Impression & Plan ready for review
- ✓Multilingual scribing across 55 languages into a clear English note

The joy of finishing on time
Be fully present in the consult. Leave your evenings for your life.
Typing while a patient talks splits your attention — and writing notes from memory at night drains the joy out of medicine. Intelligent Consult turns the conversation you already had into a structured draft waiting for your eyes.
Still charting from scratch
- –Trying to reconstruct 18 consults from shorthand scraps
- –Typing into the keyboard instead of looking at the patient
- –Referral letters and discharge summaries piled up for the weekend
Your drafts are already waiting
- ✓Walk out of each room with History, Exam, Impression, and Plan structured
- ✓Dictate a letter in 45 seconds between patients using the exact same workflow
- ✓Review, tweak with Ask Oli if needed, finalise, and copy into your clinical record
55 languages in the consult room. Your clinical note in clear English.
Turn on Translation when a consult mixes languages. OLI transcribes across 55 supported languages (English plus 54 patient-language choices) and drafts the final structured clinical note in English for your review.
Two-way live translation in the room (Beta)
See a live preview of what your patient says in English — and show your English responses in their language. Live translation is a quick preview that may miss words, and is not a substitute for an approved interpreter.
5 Evaluated patient languages
EvaluatedArabic
العربية
Cantonese
廣東話
Mandarin
中文
Tamil
தமிழ்
Vietnamese
Tiếng Việt
Plus 49 additional preview languages on our multilingual recognition path. See the complete 55-language list →
Multilingual Scribe & Live Translation · Beta
Doctors in training · Ask Oli & Reflect
A draft is something to argue with — not something to submit.
Colleges worry a scribe lets trainees stop composing. They are right to worry if the draft becomes the note. Reflect checks this draft against published sources (Plus and Delta). It does not write into the note. Hours on your CPD record exist only after you write a reflection in your own words. We do not claim this teaches clinical writing. We claim it gives you something to rewrite.

Desktop · Phone · Watch · Web
One calm workspace across every device.
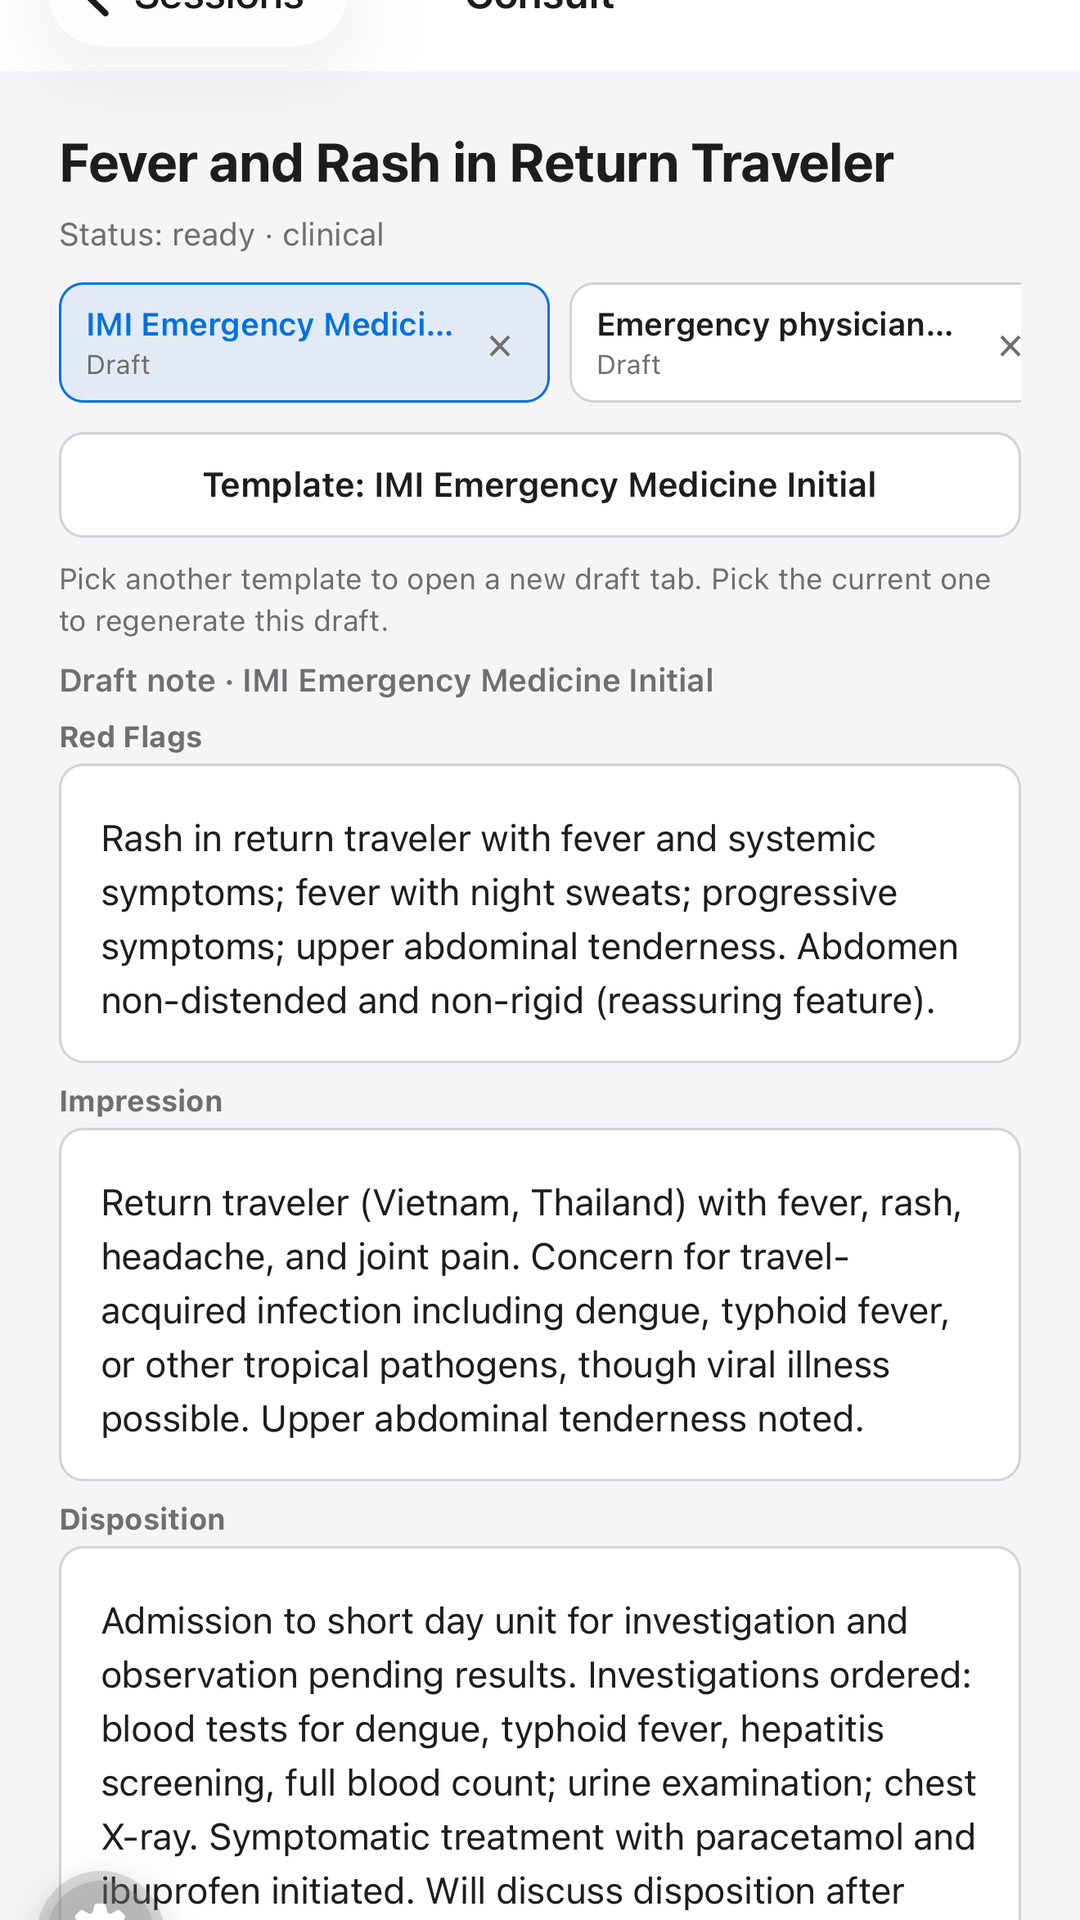
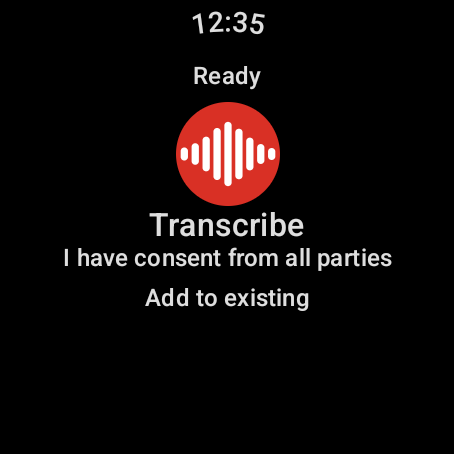
Desktop (Mac and Windows) is home — listen in the room or on a telehealth call, then review and finalise there. Phone is your pocket recorder in the room or on ward rounds. Watch records from your wrist. Web is ready when a clinic PC cannot install the app.
- ·Desktop (Mac and Windows) — home for face-to-face and telehealth (mic + call audio, no tab-share dance)
- ·Phone (iPhone & Android) — room recorder and quick draft review on the move
- ·Watch (Wear OS) — one-tap wrist recorder that lands in your desktop workspace
- ·Web console — instant fallback on any clinic computer
- ·Upload continues smoothly through brief connection interruptions
When desktop install is blocked, Chrome or Edge can still run the consult console — mic + call if you share the call tab. Safari and Firefox stay mic-only. Phone and watch captures land here too.

Privacy & trust
Built to clear clinical privacy standards.
Privacy & hosting
- Built to align with APP & GDPR
- Hosted on AWS Sydney
- No patient accounts or patient database
In every session
- Jurisdiction-aware consent attestation
- Draft for clinician review — you are the author
- Audio deleted by default after 7 days
Made in Australia. Hosted on AWS Sydney. Used around the world.
Stored in Australia. Claude and OpenAI process on their own servers, under those vendors' cross-border governance. How we host.
Ready to finish your notes before you leave clinic?
Create your free account in under a minute — then try a live consult, a 30-second dictation, or our built-in sample consult.